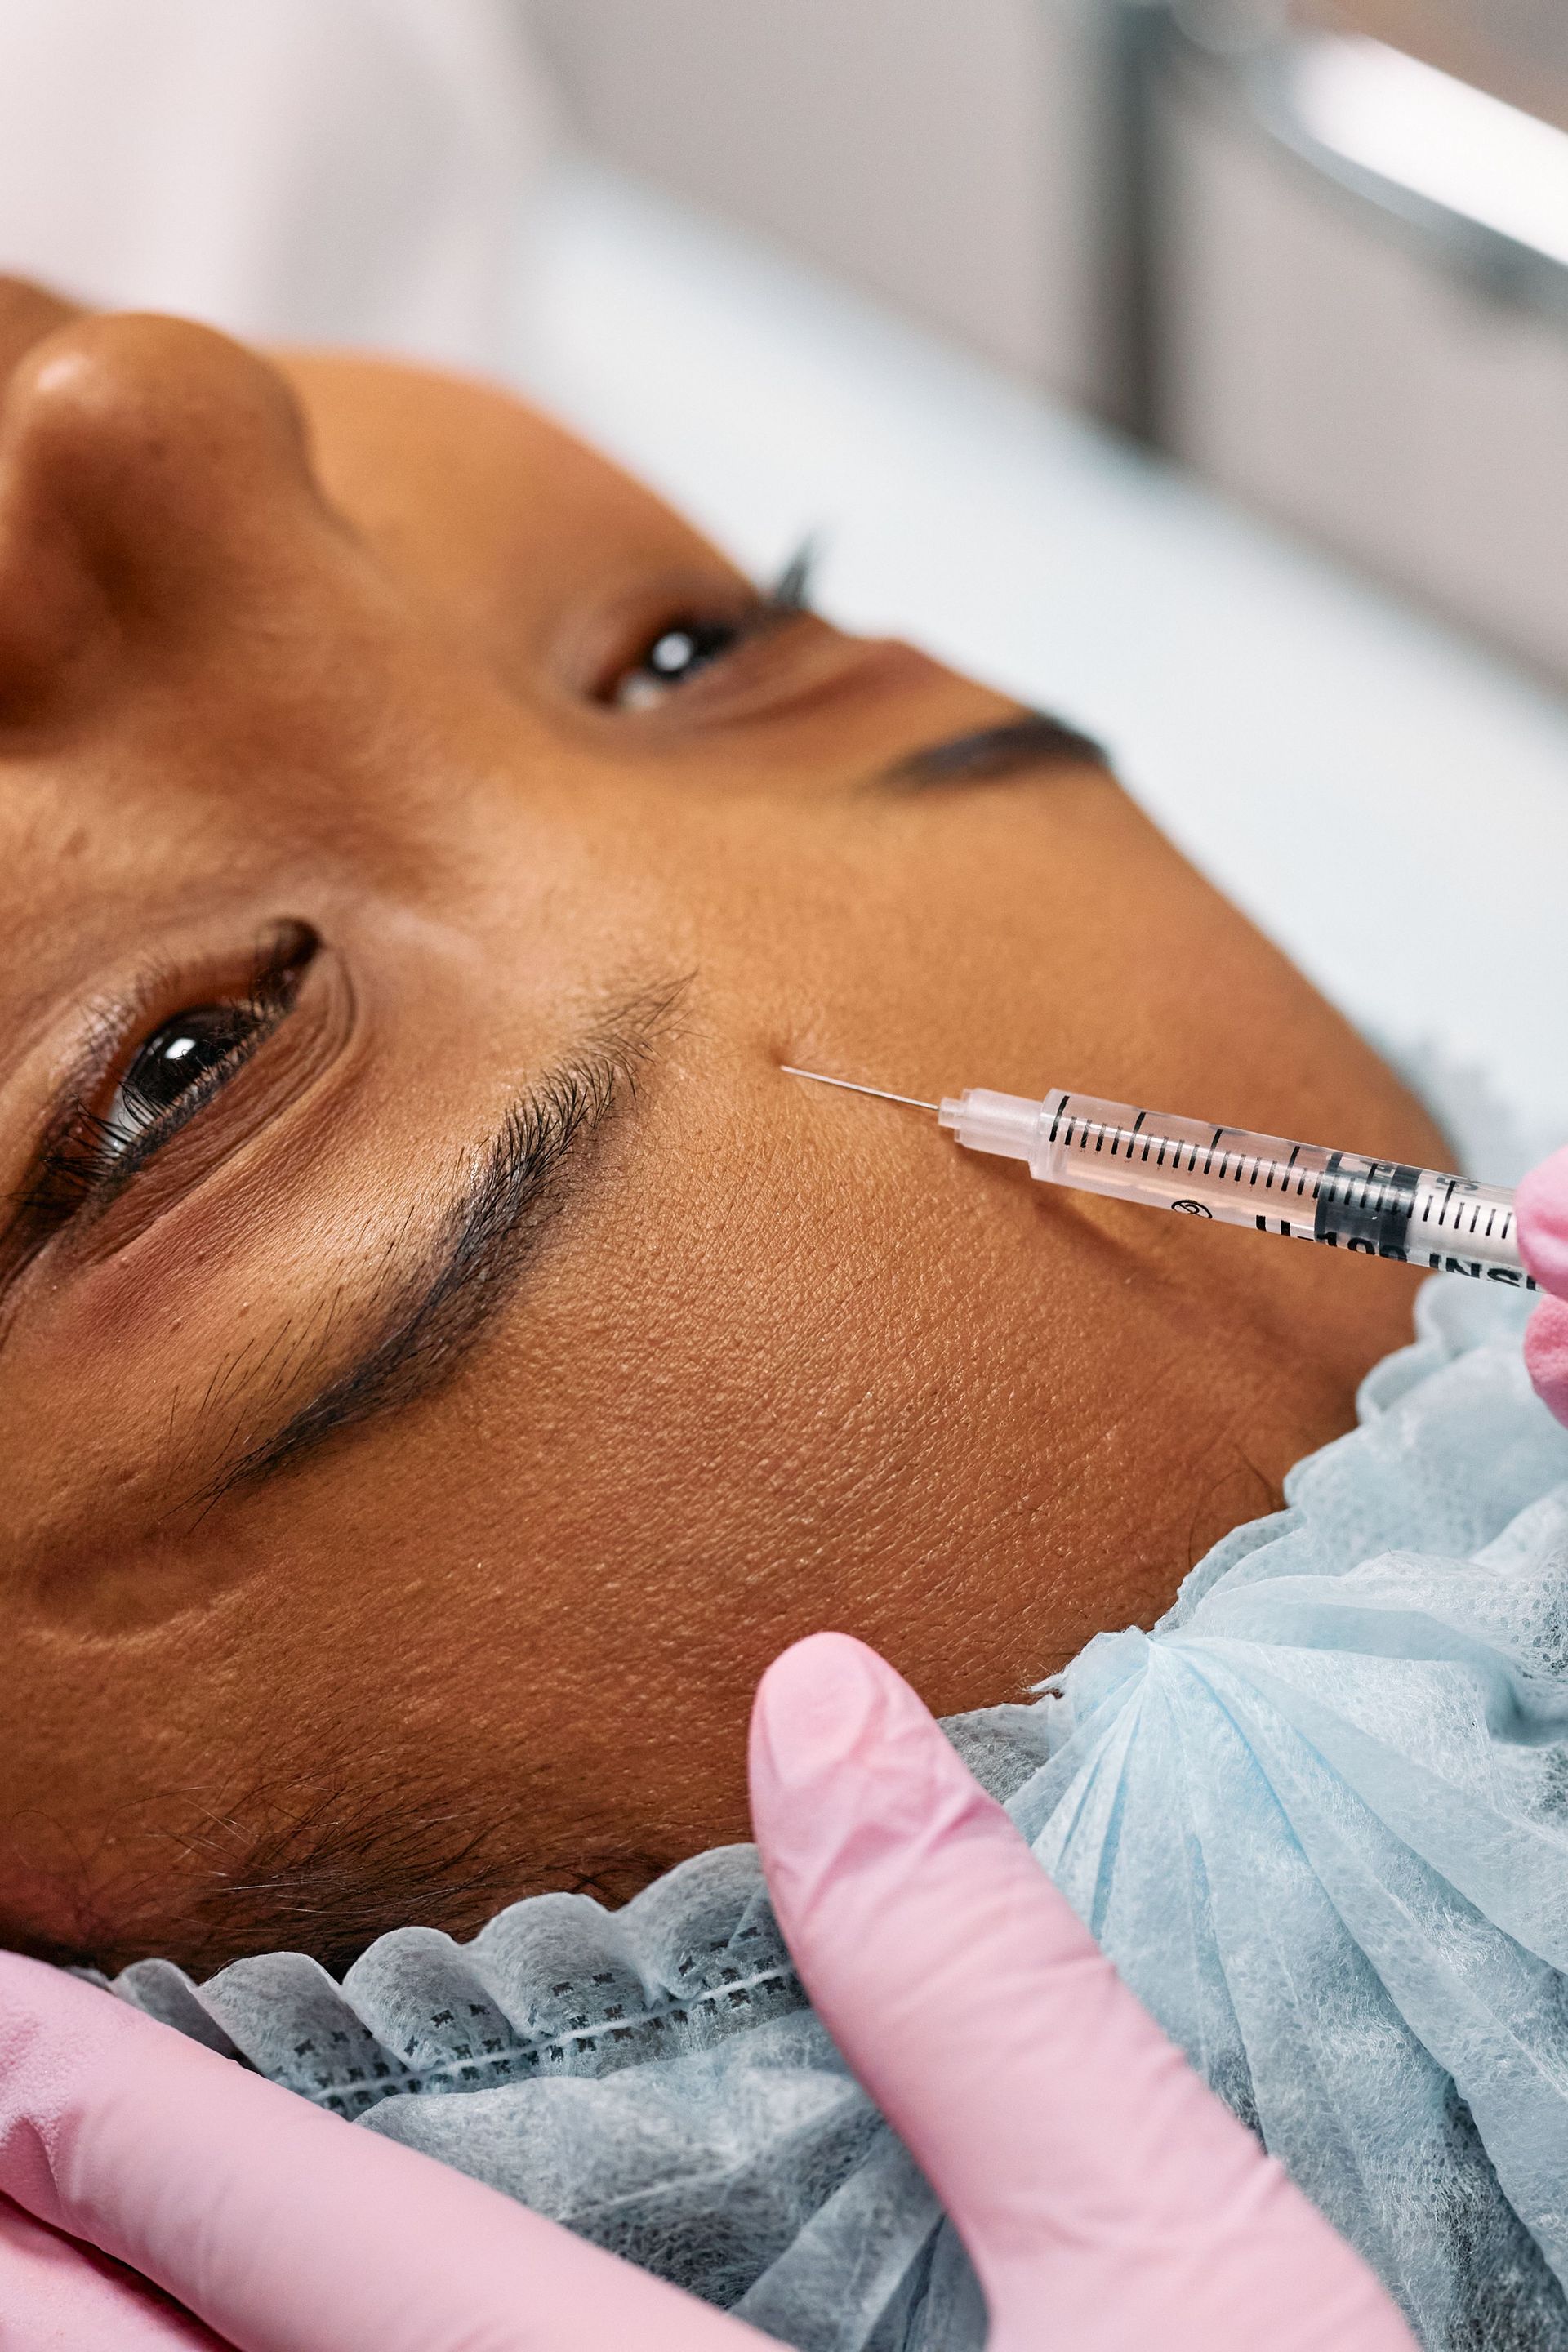
Hit a Plateau on Semaglutide or Tirzepatide? What's Normal — and What to Check Next
By Loic Assobmo, MSN, NP, AGNP — Renew Weight Loss and Med Spa, Springfield, MA
Have you been on GLP-1s but feel like you are no longer losing weight? Did you notice that when you first started the medication, it was a lot easier to lose weight — but over time, you are finding that you are not losing any weight at all?
Are you somebody who got your hands on GLP-1 medications through an online program, or through another service, and you feel like you are stuck on your own trying to figure out how to make things work?
I see this all the time at my clinic in Springfield, Massachusetts. As a med spa owner who has managed GLP-1s for weight loss for years — before all the hype — I can tell you: most of the time, the medication isn't the problem. The problem is that nobody is actively managing it with you.
Sometimes the dose — or even the medication — does need to change. But that decision should come after a provider reviews how you're taking it, what you're eating, your labs, and what else may be working against you.
Here is the truth of the matter: weight loss is not just about injecting the medication. Simply relying on the injection may seem like it is working in the beginning, but it eventually leads to plateaus. And even when it does not, it can build habits that are not sustainable — so the weight creeps back up, and the patient ends up feeling like the medication stopped working for them.
A plateau does not mean your medication quit on you. It means something needs to be checked. Below is what I check with my own patients, in the order I check it.
What counts as a plateau?
First, let us be honest about what a plateau actually is. I call it a plateau when your weight — going by weekly averages, not one weigh-in — has not really moved for about 4 to 8 weeks, even though you have been taking your medication consistently. If it has only been a week or two, that is usually just water and normal fluctuation. Give it time.
Why does the weight level off at all? A big part of it is simple math. A smaller body burns fewer calories, so the amount of food that used to make you lose weight is now just enough to maintain your new weight. Your appetite hormones also push back as you lose fat, and your metabolism slows down a little — usually about 50 to 150 calories a day, about a small snack's worth. That slows weight loss down. By itself, it does not stop it.
This is why the American Diabetes Association treats these medications as long-term therapy: your response gets reassessed regularly, your dose gets adjusted to you, and when progress stalls, you adjust the plan — you do not abandon it. So when I see a real stall, I go looking for the reason. Here is my checklist.
The plateau checklist: 7 things I check before blaming the medication
1. Are you actually on a real dose?
This is the first thing I check, and it is the one I find most often — especially with patients who come to me from online programs. These medications are not started at full strength. Per the FDA-approved dosing schedules, they start low and go up about every 4 weeks:
- Semaglutide(weight-management dosing) steps up 0.25 → 0.5 → 1 → 1.7 mg, up to a maintenance dose of 2.4 mg weekly.
- Tirzepatide starts at 2.5 mg for the first 4 weeks. Hear me on this: that is a starter dose, not a maintenance dose. From there it goes up in 2.5 mg steps, and the maintenance doses are 5, 10, or 15 mg weekly.
So if you have been on tirzepatide 2.5 mg, or a low dose of semaglutide, for months — you may not have a plateau at all. You may simply never have been brought up to a dose that works. Sometimes there is a good reason to go slow, like side effects, and the ADA is clear that the right dose is different for everybody — it is not always the highest dose. But that decision should be made on purpose, by a provider who is following you. Not by default, because nobody ever looked at your dose again. And please, do not raise your own dose — going up too fast mostly buys you worse nausea, and it is how people end up quitting altogether.
2. How are you injecting — and how are you storing it?
You would be surprised how often this is the issue. Patients are "taking" the medication, but not all of it is getting in.
- Inject into the abdomen (at least 2 inches from the belly button), the front of the thigh, or the back of the upper arm — and rotate the exact spot every week.
- Hold the pen in place until it tells you the dose is complete. If you pull away early, part of your dose stays in the pen. This takes me two minutes to check in person, and it is one of the first things I look at when a patient tells me "it is not working."
- Keep your pens in the refrigerator (36–46 °F), and never let them freeze. A pen that arrived warm in the mail, sat in a hot car, froze, or expired may not be at full strength.
- Missed doses matter too, and the catch-up rules are different for the two medications — ask your provider instead of doubling up on your own.
Reading this and realizing nobody has ever checked your dose or watched you inject? That is exactly what I do at a first visit. The consultation is free — book a free weight loss consultation and let us look at both before you blame the medication.
3. Are you eating too little? Let us talk about "starvation mode"
I hear this one a lot, so let me be straight with you. Some people assume that to lose weight on these medications, you have to barely eat. And there is a popular idea that if you eat too little, your body goes into "starvation mode," starts storing everything as fat, and refuses to lose. That is not really how it works — in controlled studies, people eating very little keep losing weight, and the metabolic slowdown is only about 50 to 150 calories a day. It slows you down. It does not stop you, and it does not make you store fat out of nothing.
But — and this is important — eating far too little on a GLP-1 is still a real problem. Just for different reasons:
- You lose muscle along with the fat. If you are not getting enough protein and not doing any strength training, a meaningful share of the weight you lose will be muscle, not fat. And less muscle means your body burns fewer calories every day — which makes the next pounds harder to lose, and the regain easier.
- You come up short on nutrition. These medications already cut how much you eat by a lot. If on top of that you are skipping meals all day, you can end up short on protein, iron, calcium, and vitamins — and dealing with hair loss, fatigue, constipation, and gallstones from losing too fast. The ADA specifically tells providers to watch for exactly this.
- You cannot keep it up. Barely eating works for a few weeks. Then your appetite breaks through, you rebound, and the weight comes back — and that is when patients tell me "the medication stopped working."
So the answer is not to force yourself to eat more to "restart" your metabolism. The answer is to eat enough of the right things. The current guidance from the American College of Lifestyle Medicine, the American Society for Nutrition, the Obesity Medicine Association, and The Obesity Society is about 1.2 to 1.6 grams of protein per kilogram of body weight a day while you are actively losing — or, to keep it simple, roughly 80 to 120 grams of protein a day, spread out at about 25 to 40 grams per meal. And protein by itself is not enough: that same guidance pairs it with strength training at least 3 times a week, because that is what actually protects your muscle. Your exact number depends on your weight, your kidneys, and your health history — that is a conversation we have at your follow-up, not something to guess at.
This is something we go over at every monthly follow-up at Renew: are you eating too little, are you eating too much, and are you eating the right amount of the right foods. Most patients on their own have never had anybody check.
4. Or are you eating more than you think?
The other side of it is just as common. Did you know that certain foods are more satiating than others? Certain foods keep you full for much longer — and others barely register. Liquid calories, sauces and oils, grazing in the evening when the medication's effect is wearing off late in the week, weekends — that is where it usually hides. When a patient sits with me and we honestly walk through a few days of eating, the reason for the stall usually shows up in about five minutes. Protein first, more fiber, real food over processed food — that is what works with the medication instead of around it.
5. What about alcohol?
Did you know alcohol consumption can affect how well these medications work? I consistently see clients from our own community come into my clinic and tell me the medication is not working for them — and sometimes, a minor tweak of their alcohol intake is all that is needed to get the benefits they want from it.
Now, to be accurate: alcohol does not cancel out your injection, and the medication labels do not say you cannot drink. But alcohol is about 7 calories a gram — roughly 100 calories in one standard drink before any mixers — nobody counts it, it makes you eat more afterwards, and it ruins your sleep. A few drinks, a few nights a week, can quietly erase the whole deficit the medication created. It also tends to hit harder on a GLP-1 — more nausea, more reflux, more dehydration — and if you also take insulin or a sulfonylurea, alcohol raises your risk of low blood sugar and can mask the symptoms. Look at the alcohol honestly before you blame the dose.
6. Sleep, your other medications, and your health
A few more things I check that most people never think of:
- Sleep. In the research, short sleep made people eat roughly 385 extra calories the next day, on average. Getting more sleep did the opposite. Aim for at least 7 hours — and if you snore heavily or wake up tired, tell me. Sleep apnea is common, it is treatable, and it works against weight loss.
- Your other medications. Some common medications push weight up: insulin and some older diabetes medications, steroids, certain antidepressants and antipsychotics, some seizure and pain medications, even the sedating antihistamines people take to sleep. Never stop one of these on your own — but a provider who reviews your full list can often find a weight-neutral alternative.
- Your health. Checking the thyroid once during a weight evaluation is reasonable — but underactive thyroid usually only causes a modest amount of weight, much of it fluid, so fixing it rarely explains a big stall. PCOS is different: it genuinely interacts with weight and changes how we manage things. But honestly? Most plateaus are not a hidden hormone problem. Most of the time, it is items 1 through 5 on this list.
7. Sometimes it is just time — or you have arrived
Some people are simply slower responders. The ADA frames the first months on these medications as an assessment period for a reason: we look at your response, we individualize the dose, and we adjust — we do not declare the treatment a failure at the first flat month. And if your weight has leveled off after you have already lost a good amount, you may be at the point where the right conversation is maintenance, not failure. What I will tell you plainly is this: stopping the medication because you hit a plateau usually means regaining a significant amount of the weight back — the ADA is firm on that, because these are long-term medications. A plateau is a reason to adjust the plan. It is not a reason to throw away your progress.
So when do we change the dose — or change the medication?
If we have checked your dose, your injection, your protein, your alcohol, your sleep, and your medication list, and you are still stuck, then yes — we have real options. Adjusting your dose within the approved schedule, treating something that is working against you, or, for some patients, discussing a change of medication altogether. Those decisions depend on your whole picture: what you have tried, what you can tolerate, your other conditions, your other medications, and what is covered for you. There is no do-it-yourself version of that decision, and no responsible provider makes it off a refill form. That is the kind of judgment call that should not be made alone — or by an algorithm.
When to get help promptly — do not wait for a monthly check-in:
- Severe or persistent stomach pain, especially spreading to your back, with or without vomiting — could be pancreatitis. Stop the medication and get urgent care.
- Vomiting or diarrhea where you can't keep fluids down, very low urination, dizziness or fainting (dehydration).
- Pain in the upper right abdomen with fever or yellowing of the skin or eyes (gallbladder).
- Swelling of the face, lips, or tongue, or trouble breathing (serious allergic reaction) — emergency care.
- A lump or swelling in your neck, persistent hoarseness, or trouble swallowing — report promptly. (These medications carry an FDA boxed warning about thyroid C-cell tumors seen in rodents; they must not be used by people with a personal or family history of medullary thyroid carcinoma or MEN 2 syndrome.)
- Also call your provider promptly for: low-blood-sugar symptoms if you take insulin or a sulfonylurea; any planned surgery or procedure (these medications slow stomach emptying — your anesthesia team must know); pregnancy planning; or if you've missed 2 or more doses.
The real risk isn't the medication — it's being left to manage it alone
Whether a GLP-1 comes as a brand-name pen or is compounded through a licensed pharmacy, the medication is only half the treatment. The other half is screening before you start, a dose that's actually titrated, someone checking your injection technique, labs and nutrition along the way, and a clinician you can reach when something feels wrong. That's the part many online programs skip — the box arrives, and you're on your own. It is worth checking who stands behind any program you use: a real prescriber who evaluated you, a licensed pharmacy you can identify, and follow-up that actually happens. If your current program offers none of that, a stall isn't a surprise — it's the predictable result of medication without management.
What we do differently at Renew
At Renew Weight Loss and Med Spa, we do not just prescribe medication. Our providers work with you to build a personalized plan, and then we stay with you — because overall, I have found that proper weight loss on these medications still requires a provider's expertise and guidance. At your monthly follow-ups, we review your dose, we watch how you are injecting, we go through what you are actually eating, and we plan for maintenance before you ever get there — so that you not only lose the weight, but keep it off long-term.
We are at 235 Chestnut St, Office 12, in Springfield, and our patients come to us from across the Pioneer Valley — Chicopee, Holyoke, West Springfield, Agawam, East Longmeadow, Longmeadow, Ludlow, and Wilbraham.
So if any of this resonates with you — if you are on a GLP-1 and the weight loss has stopped, or you are on one and figuring it out completely on your own — I invite you to book a consultation with us at Renew. Consultations are free. You will get honest, expert guidance on how to properly lose weight on these medications, and a plan built around you. You can read more about our medical weight loss program in Springfield, and when you are ready, book a free weight loss consultation. If medication with us is right for you, our programs start at $299/month, and the price stays flat — it does not go up as your dose goes up.
Frequently asked questions
Is a GLP-1 plateau normal?
Yes — very normal. Weight loss on semaglutide and tirzepatide is fastest in the beginning and levels off over time. That is the expected pattern with these medications, and it is exactly why they are managed as long-term therapy with regular follow-ups. A plateau is not proof that your medication failed.
How long does a plateau last?
There is no fixed answer. If the reason is your dose, your injection, your protein, your alcohol, or your sleep, weight loss often starts moving again within a few weeks of fixing it. If you have leveled off after losing a good amount at your current dose, then the conversation becomes dose adjustment, a possible change of medication, or maintenance — and those are decisions to make with your provider.
Should I just increase my dose?
Not on your own. Plenty of people who think they have plateaued are actually still sitting on a starter or low dose — and for them, a provider-led increase is exactly the answer. But going up too fast, or higher than you can tolerate, mostly means worse side effects and people quitting. The ADA notes that the best dose for you may not be the maximum dose. Dose changes belong with the provider managing your care.
I'm barely eating. Should I eat more to break the plateau?
Eating more does not restart your metabolism — that slowdown is only about 50 to 150 calories a day. But eating far too little does hurt you in a different way: it costs you muscle, protein, and nutrition, and it usually ends in rebound eating. The goal is enough protein and enough total food to protect your muscle while you lose. That is a target your provider should set with you.
Can I switch medications if I've stalled?
It is an option your provider may discuss — after your dose, your technique, and the rest of this checklist have been reviewed. There is no conversion chart between these medications, so switching means starting a new titration schedule over again, under supervision. Never take two GLP-1 medications together, and do not switch through a program that will not follow you afterwards.
I got my medication online. Can Renew still help me?
Yes — honestly, that is a large part of who I wrote this article for. Bring your medication history to a free consultation and we will review your dose, your technique, your labs, and your habits, and I will tell you straight what I would do differently. You can see what an in-person follow-up at Renew actually covers on our medical weight loss page.
References
- American Diabetes Association Professional Practice Committee. Obesity and Weight Management for the Prevention and Treatment of Diabetes: Standards of Care in Diabetes — 2026, Section 8. Diabetes Care , 2026.
- Mozaffarian D, et al. Nutritional priorities to support GLP-1 therapy for obesity: joint advisory of the American College of Lifestyle Medicine, the American Society for Nutrition, the Obesity Medicine Association, and The Obesity Society. Obesity , 2025.
- U.S. Food & Drug Administration. FDA-approved prescribing information for semaglutide and tirzepatide (dosing schedules, boxed warning).
- Al Khatib HK, et al. The effects of partial sleep deprivation on energy balance: systematic review and meta-analysis. European Journal of Clinical Nutrition , 2017.
- Müller MJ, et al., and Martins C, et al. — research reviews on metabolic adaptation (adaptive thermogenesis) after weight loss, as summarized in the 2025 joint advisory and ADA Standards above.
This article is educational information from Renew Weight Loss and Med Spa and is not medical advice. It doesn't create a provider–patient relationship. Don't start, stop, or change the dose of any medication without your prescriber. If you have any of the urgent symptoms listed above, seek care immediately.
Search Spa Services
Schedule Session
Questions? Contact our office by phone or book an appointment online.
Questions? Call our office:
(413) 438-5737